
Strength Training During Perimenopause and Menopause: What Changes?
The dumbbells have not changed. The workout is familiar. But after another night of waking at 3am in the morning, the session feels considerably harder than it did last month. For some women, perimenopause first becomes noticeable in situations like this. Recovery feels less predictable, periods become irregular, a routine that once fitted neatly into the week now competes with fatigue, night sweats or a calendar already full of other people's needs.
Then comes the advice: lift heavy, avoid stress, do more cardio, do less cardio. Somehow, a changing body becomes another project to manage perfectly.
Strength training offers something more useful than another set of rigid rules. It can improve strength after menopause, support physical function and, with appropriate loading, benefit bone health. The basic principles remain familiar: practise useful movements, gradually increase the challenge and allow recovery. What may need more attention is how you make those principles work in your life.

What actually changes during the menopause transition?
Perimenopause is the transition around the final menstrual period, when hormonal fluctuations and changes in cycle patterns can occur. Natural menopause is confirmed after 12 months without a period when there is no other cause. A clinical review of perimenopause describes the considerable variation in symptoms and hormonal changes during these years. Body composition can change too, sometimes without a dramatic change on the scale.
In the Study of Women's Health Across the Nation, researchers tracked body composition across the menopause transition. The rate of fat gain accelerated while lean mass began to decline. These patterns continued until approximately two years after the final menstrual period, then levelled off in the study's models.
The rate of weight gain itself did not accelerate at the start of the transition. That distinction helps explain why weight alone can miss changes happening underneath it.
Lean mass also includes more than skeletal muscle. These findings describe population averages, rather than predicting what will happen to every woman or establishing that hormones explain every change in her body.
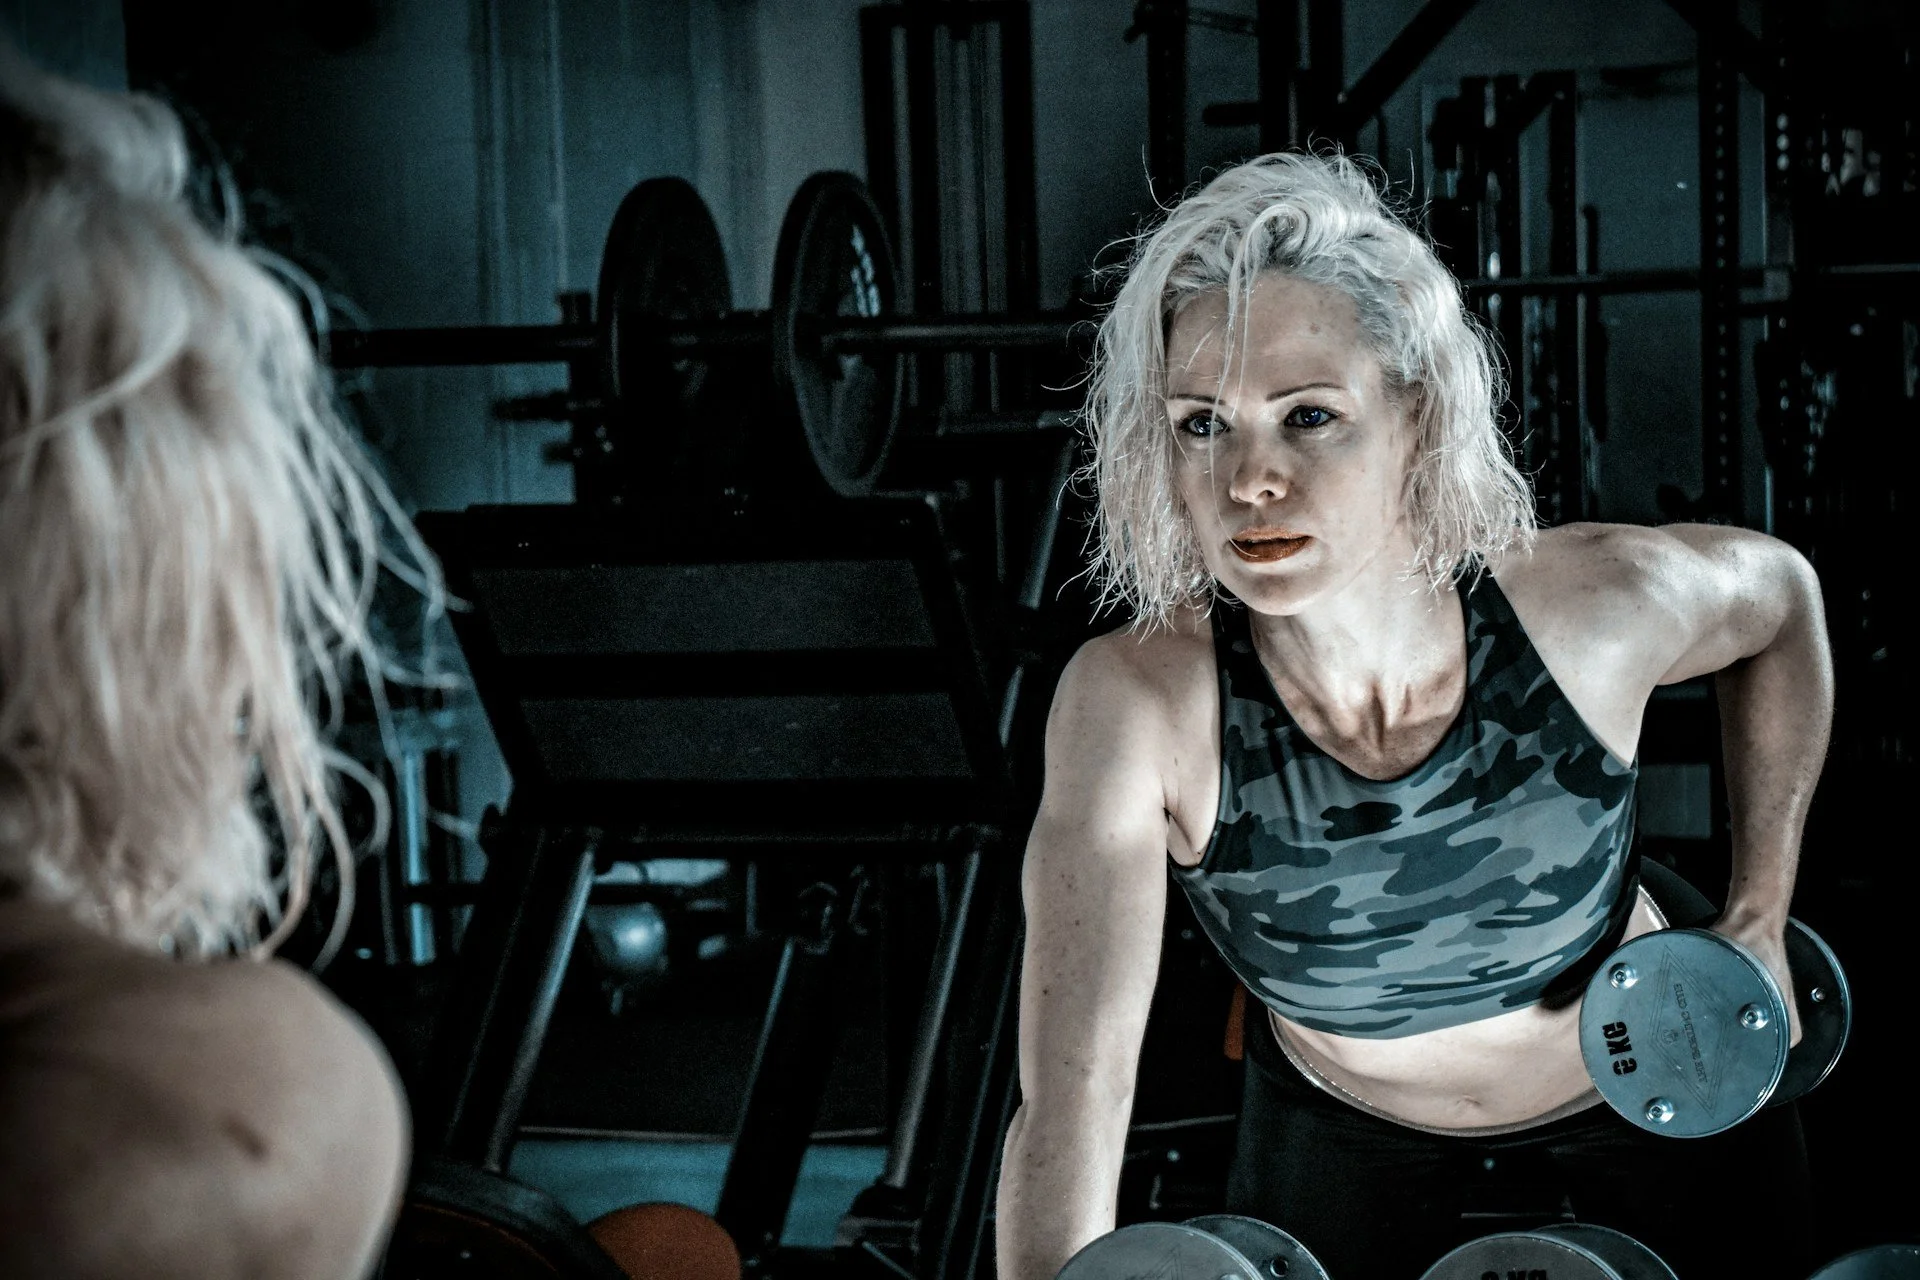
Your muscles can still respond to training
The encouraging result is straightforward: women can gain strength both before and after menopause. A 2026 systematic review involving 4,019 women found substantial strength improvements with resistance training in both premenopausal and postmenopausal groups. The analysis found no statistically significant difference between those groups in the size of the strength response.
That does not establish identical results for every age or training programme. It does challenge the idea that passing through menopause makes meaningful progress unlikely. There is an evidence gap to acknowledge here. Comparisons of premenopausal and postmenopausal women do not answer every question about training during the often unpredictable perimenopausal years.
Still, you do not need a perfectly settled hormonal environment before beginning. Progress might mean lifting a heavier bag comfortably, managing stairs more easily or adding repetitions to an exercise that used to feel difficult. Those are useful outcomes at any stage.
Bone health gives strength training another purpose
The LIFTMOR randomised trial provides a particularly clear example of what carefully supervised training can achieve. Researchers studied 101 postmenopausal women with low bone mass. One group completed eight months of supervised, twice-weekly resistance and impact training. The comparison group followed a lower-intensity home programme.
Lumbar spine bone mineral density increased by an average of 2.9% in the supervised group and declined by 1.2% in the comparison group. The supervised group also improved measures of physical function more. These were screened participants receiving close supervision. The result supports appropriate loading as a useful tool for bone health; it does not mean someone with osteoporosis should immediately copy heavy lifts or jumping exercises from a video. The study measured bone density and function, rather than demonstrating fewer fractures.
If you have osteoporosis or a previous fragility fracture, ask a clinician or physiotherapist familiar with bone health to help adapt exercise selection and progression.
Start with a week you can repeat
Two full-body strength sessions can be a practical place to begin. The World Health Organization's activity guidelines recommend strengthening all major muscle groups on at least two days each week, alongside aerobic activity. For someone returning after a break, Monday and Thursday might include a squat or leg press, a hip hinge, a row, a chest press and a simple carry or trunk exercise. Machines, dumbbells and other equipment can all have a place.
An introductory version might involve one or two controlled sets of each exercise, using a manageable repetition range such as eight to twelve. This is an example to adapt with a coach, rather than a menopause-specific prescription.
Choose movements you can perform comfortably and understand well enough to repeat. Keep a short record of the exercise, weight and repetitions. A familiar programme gives you a way to see improvement that an entirely different workout every visit cannot easily provide.
Make the work challenging enough to progress
Using the same light weights indefinitely can eventually leave too little challenge to drive further improvement.
The 2026 American College of Sports Medicine position stand supports progressive resistance training and finds that heavier loads can enhance maximal strength gains. It also reports that taking every set to momentary muscle failure does not consistently improve outcomes. For a beginner, a useful working effort might leave a couple of controlled repetitions available at the end of a set. You should be working, while still controlling the movement.
Suppose you begin a row with a weight you can lift eight times comfortably. Over several sessions, you build towards twelve controlled repetitions. Once that feels manageable, a small weight increase can provide the next challenge. The appropriate weight depends on the exercise and your experience. There is no single dumbbell size that makes a workout suitable for menopause, and improvement does not require a personal best every session.

Let symptoms inform the day's workload
A demanding session after several disrupted nights may feel different from the same session after good sleep. That is useful information when planning what to do next. Consider keeping a shorter version of your programme: the main exercises, fewer sets and a little more rest. On a difficult day, completing that version may be more realistic than attempting your longest workout. On other days, resting may be the better choice.
A brief training log can help you notice patterns. Record sleep quality, symptoms and how the session felt alongside the weights. Look across several weeks before deciding that your whole programme has stopped working. These are practical adjustments, rather than a proven hormone-based training formula. They leave room for the variation between women and between days.
Persistent pain, unusual fatigue or symptoms that regularly disrupt daily life deserve assessment. A gym programme can be adapted while you get help; you do not have to solve every symptom through exercise.
Keep aerobic activity in the picture
Strength training can sit comfortably alongside walking, cycling, swimming or a class you enjoy. A review of 101 studies involving 5,697 postmenopausal women found that exercise improved body composition overall. Resistance and combined training showed greater benefits for muscle-related outcomes, while aerobic and combined training showed greater benefits for fat-related outcomes.
These findings support combining activities according to your goals. They do not establish one ideal weekly formula or guarantee a particular change in body shape.
A week containing two strength sessions, regular brisk walks and an enjoyable weekend activity can give each type of exercise a place. Build the amount gradually, especially if you are starting from very little activity. A programme becomes easier to sustain when it includes movement you look forward to.

Eat enough to support the work
Training creates a reason for muscles to adapt. Food helps provide the resources for that adaptation. The International Society of Sports Nutrition's protein position stand describes approximately 1.4–2.0 grams of protein per kilogram of body weight daily as sufficient for most exercising adults. This is general exercise guidance, rather than a requirement unique to menopause.
A useful first step is to look at meals you already eat. Could breakfast include Greek yoghurt, eggs or tofu? Does lunch contain a substantial protein source? Include carbohydrates and enough overall food to support training as well. You do not need to turn every meal into a calculation. If you are unsure how to balance muscle goals with a health condition or a change in appetite, a registered dietitian can help personalise the approach.
Exercise has benefits without being a cure for every symptom
Some findings on symptoms are promising. In a 15-week resistance-training trial, the training group reported an average reduction of about 44% in moderate or severe hot flushes, compared with about 2% in the control group. Fifty-eight women completed the trial and were included in the analysis. However, the Menopause Society's 2023 evidence review did not recommend exercise as a specific treatment for hot flushes because the overall evidence was insufficient or inconsistent.
You can value strength training and still seek treatment for disruptive symptoms. An exercise programme does not need to resolve everything to be worthwhile.
Begin with a manageable week, learn the movements and give yourself time to improve. If you would like support getting started, explore training options at VIMALIFE. The next useful milestone might be a more confident lift or an easier flight of stairs, even while other parts of this transition remain unpredictable.
